Eyelid problems — drooping lids and lids that will not close
Two common eyelid problems work in opposite directions. In one, the upper lid hangs down (ptosis) and can block sight. In the other, the lids cannot close fully (lagophthalmos), so the eye dries out. A sudden change in an eyelid always needs a doctor quickly.
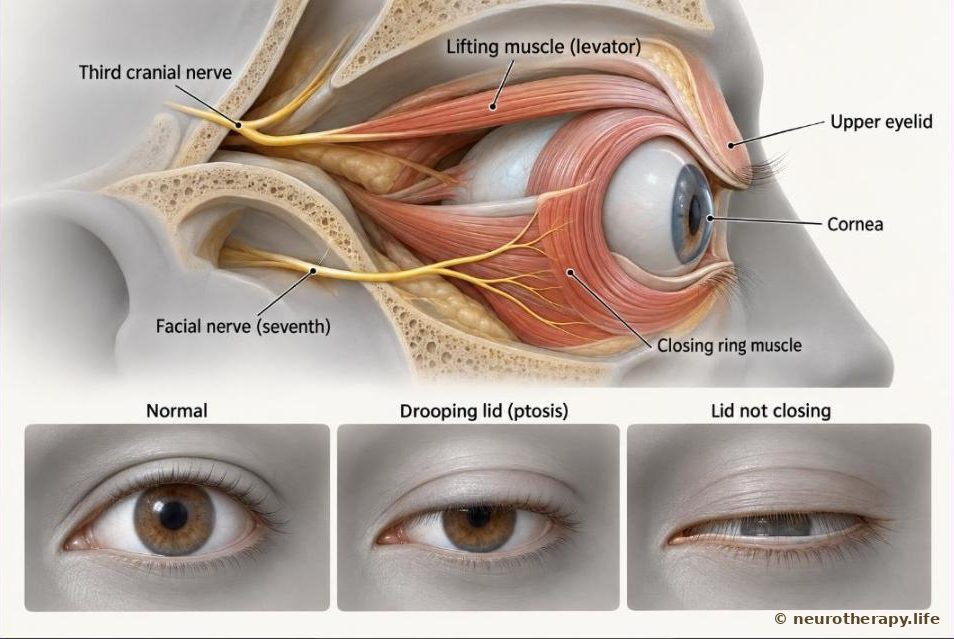
- The upper lid is lifted mainly by one muscle, run by the third cranial nerve
- Closing the eye is the job of a ring muscle run by the facial (seventh) nerve — which is why Bell's palsy can stop an eye closing
- A drooping lid in a child, left untreated, can lead to a “lazy eye”
Source: MedlinePlus; Cleveland Clinic; StatPearls (NCBI)
What is Eyelid problems — drooping lids and lids that will not close?
Every blink uses two teams. A long muscle at the top of the eye socket lifts the upper lid; the third cranial nerve tells it when to work. A ring of muscle around the eye closes the lids; the seventh, or facial, nerve controls it. Blinking spreads tears over the eye and keeps it clean and wet.
When the lifting side is weak — from age, a muscle that formed weakly before birth, an injury, or a nerve problem — the lid droops. This is ptosis. When the closing side is weak — most often because the facial nerve is not working, as in Bell's palsy — the lids cannot shut fully. This is lagophthalmos. Then the front of the eye (the cornea) stays exposed and can dry, get sore and even scar.
What are the symptoms?
- An upper lid that sits lower than the other, sometimes covering part or all of the pupil
- Tilting the head back or raising the eyebrows to see — children often do this
- Tired, aching eyes and extra watering
- An eye that does not close fully, especially during sleep
- A dry, gritty, red eye, blurred vision or discomfort in bright light
What causes it, and who is more likely to get it?
The lifting muscle
- Age: the lifting muscle stretches or comes away from the lid
- A lifting muscle that formed weakly before birth
- Injury, earlier eye surgery, or a swelling, stye or growth weighing the lid down
Nerves and muscle signals
- Damage to the nerve that lifts the lid — from diabetes, a stroke or a growth; Horner syndrome
- Myasthenia gravis, where the message from nerve to muscle gets weak
- Facial nerve weakness — Bell's palsy, stroke, infection, injury or a growth — stops the lids closing
Damage to the lid itself
- Scarring from burns, chemicals or sun damage, or after eyelid surgery
- Very loose, floppy lids
How is it found?
An eye doctor looks at the lid, measures how high it sits and how well it closes, and checks the eye's movements and pupils. The cause decides the care, so a new droop or a lid that suddenly will not close is checked soon.
Eye examination
The doctor measures the lid height and the gap when the eyes close, counts the blinks, and looks closely at the eye with a slit-lamp microscope.
Visual field test
Shows how much of the upper view a drooping lid is blocking.
Eye movement test
The eye follows a target in every direction; a weak nerve shows up as an eye that will not turn one way.
Tests for myasthenia gravis
When the droop comes and goes, special tests check whether the message from nerve to muscle is weak.
A neurotherapist first asks when the change began — a sudden one goes to a doctor before anything else — and reads the doctor's reports. Then the therapist watches the eyes: which lid is affected, whether it hangs down or will not close, and which way the eye itself is pointing.
How Neurotherapy sees Eyelid problems — drooping lids and lids that will not close
In LMNT teaching, each of the twelve nerves that leave the brain has its own Medulla count. The eyelids have two: the third nerve lifts the upper lid, so a drooping lid — or eyes that stay shut — is given (3) Medulla; the seventh nerve closes the lids, so lids that will not close properly, as in Bell's palsy, are given (7) Medulla. Other problems of the eyelids are given (5) Medulla, the count of the nerve that carries feeling from the face and lids. Guruji's teaching is to read the eye, not the word — the finding chooses the number.
How LMNT teaching reads an eyelid problem
- Look at the eyeIs the lid hanging down, or failing to close? Where is the eye pointing?
- Lid hangs downThe lifting nerve — the third — is read as weak: (3) Medulla
- Lid will not closeThe closing nerve — the seventh — is read as weak: (7) Medulla
- (15) Medulla firstAlways before any Medulla given for a nerve of the head
- Three roundsA minute and a half apart — then record what the eye can now do
LMNT teaching gives (15) Medulla to help the body make acetylcholine, the chemical that carries the message from nerve to muscle. It names myasthenia gravis — where the lids droop by themselves — among the conditions in which patients have been seen to benefit. Guruji marked the link between (3) Medulla and myasthenia gravis with a question mark: his own thinking, left open for research.
Neurotherapy treats according to the condition of the body.
Neurotherapy treatment for Eyelid problems — drooping lids and lids that will not close, step by step
Examine first — the eye, not the word
The therapist asks when it began and reads the doctor's reports. A sudden droop, or one with double vision, pain or weakness elsewhere, goes to a doctor first. Then the therapist watches which lid is affected and which way the eye points.
(15) Medulla first
(15) Medulla is given on both sides of the neck below the ears, before any Medulla count for a nerve of the head.
The count the finding chooses
A drooping lid, or eyes that stay shut: (3) Medulla. Lids that will not close properly: (7) Medulla. Other problems of the eyelids: (5) Medulla.
Three rounds, and a record
Each Medulla count is given three times, a minute and a half apart. The therapist notes what changes — how high the lid sits, whether the eye closes in sleep — and keeps the doctor informed.
Points and formulas used
(15) Medulla
(15) Medulla — the acetylcholine treatment; always given first, before any Medulla count for a nerve of the head.
Open →Never do this
- A lid that droops suddenly — or droops with double vision, eye pain, a severe headache, one large pupil, a weak arm or leg, a fallen face or slurred speech — is an emergency. Call 108 / 112 first. Nothing is given. Stroke, or a passing weakness, numbness or loss of vision, within three months
- A droop that comes and goes and gets worse by evening needs a doctor. If it comes with trouble breathing or swallowing, go to hospital at once. Myasthenia gravis
- An eye that will not close dries out and can get ulcers and scars. Use the drops, ointment and night-time tape your doctor advises. A red, painful eye or blurred vision needs a doctor the same day. Eyes
- A child with a drooping lid should see an eye specialist soon — early care prevents a lazy eye. Children get half the adult dose and light treatment only, given by a trained therapist.
- Cancer: if the person has cancer, (10) Pan, Thymus, Pit, Lu + Sh, Rt. Ov / Lt. Ov and (30) Medulla are never given — the therapist changes the plan.
- Keep taking the medicines your doctor prescribed. Neurotherapy works alongside your medical care, never instead of it.
From Ayurveda and the kitchen
Test yourself
What research says
- Strong evidence
This medical reference explains how the lid is lifted: mainly by the levator muscle, run by the third cranial nerve, with a small extra lift from a muscle worked by the body's automatic nerves. A droop can come from the muscle, the nerve, the lid's attachment, a weight on the lid or an injury.
- Strong evidence
Closing the eye depends on the orbicularis oculi muscle, run by the facial (seventh) nerve. When that nerve is paralysed — as in Bell's palsy — the lids cannot shut, the front of the eye is exposed, and a full blink is needed to keep a healthy tear film.
No clinical trial of Neurotherapy for eyelid problems has been published yet. Improvements reported by neurotherapists are clinical observations.
For you
Older adults
A lid that slowly droops with age is common, but if it starts to block your view, see an eye doctor. Any sudden change is checked the same day.
Parents
If your child tilts the head back to see or one lid sits low, take the child to an eye specialist early — protecting the sight comes first.
If your eye will not close
Protect it day and night with the drops, ointment, tape or goggles your doctor advises, and tell the therapist how it closes in sleep.
This page explains; it does not diagnose. Neurotherapy works alongside your medical care — keep taking the medicines your doctor prescribed, and see a doctor for any new or severe symptom.